For Professionals Who Care Deeply

Feeding Therapy Referral Made Easy | Foodology Feeding Therapy

You're doing everything you can. But you can't do it all.

As a pediatrician, therapist, or school provider, you care deeply about your families — but feeding concerns? They're messy, complex, and time-consuming.

You've probably been there:

  • A child eats five foods… but they're still growing
  • A parent insists something is wrong… but you don't see a clear medical diagnosis
  • You want to help… but you're out of time, tools, or referrals

That's where a trusted feeding therapy referral makes all the difference. You want to support them. But you also don't have 45 minutes to explain sensory feeding aversions, oral motor delays, or ARFID.

That's where Foodology Feeding steps in — and it looks a little different depending on where you're sitting. Jump to the checklist and scripts built for your role below.

Not Sure Who Should See This Case?

Who do I see for this?

Feeding concerns don't always fall neatly into one specialty. This is the chart our own team uses when a symptom could point to a few different directions.

Chart showing which specialist to see for different feeding symptoms — feeding therapist, dietitian, or psychologist
01 · Pediatricians & PCPs

Spot the red flags at well visits. Refer without needing a diagnosis first.

Feeding issues are often dismissed as "just picky eating." Left unaddressed, they can spiral into nutritional deficiencies, anxiety, ARFID, or Pediatric Feeding Disorder. You don't need a formal diagnosis to refer — a pattern of concern is enough.

Ask about at the well visit

  • Eats fewer than 20 total foods
  • Eliminates entire food groups or textures
  • Refuses previously accepted foods and doesn't regain them
  • Gags, vomits, or cries in response to food exposure
  • Insists foods be prepared exactly the same way every time
  • Shows extreme rigidity, anxiety, or panic at meals
  • Ongoing constipation, reflux, or suspected food sensitivities
  • Stuck at a feeding milestone (e.g., never progressed from purées)
  • Avoids eating in front of others or at school
  • Infants: latch/bottle difficulty, poor weight gain, suspected tongue or lip tie, feeding fatigue, rough transition to solids

Do's & don'ts

Do

  • Ask "Tell me about mealtimes at home" — open-ended, not yes/no
  • Refer based on pattern of concern, even without a clean diagnosis
  • Run bloodwork: CBC, iron, zinc and copper
  • Refer to an allergist to rule out black and white food allergies
  • Track growth trend over time, not just today's percentile
  • Validate the parent's gut feeling, even if labs look normal

Don't

  • Say "they'll grow out of it" without asking about the pattern
  • Rule out concern just because growth curve looks fine
  • Wait for weight loss before referring
  • Tell parents to "just keep offering" with no concrete plan
Say this instead
"A lot of families I see are dealing with something similar — I want to connect you with a feeding specialist who can dig into this with you, no matter what we find."
📦 Want printed copies for your office? Just let us know — we'll send them.
02 · Dietitians & Nutritionists

When nutrition education isn't translating to intake, the barrier usually isn't nutritional.

You can build the "perfect" meal plan and still watch a child refuse it. That's usually a sign the barrier is sensory, oral-motor, or nervous-system based — not a knowledge gap.

Red flags to watch for

  • Nutrient or variety goals stall despite a solid nutrition plan
  • Parent reports mealtime battles even when the plan looks "textbook"
  • Client is resistant to any exposure-based or behavioral coaching
  • Suspected sensory component behind refusal (texture, smell, temperature)
  • GI symptoms — constipation, reflux, bloating — alongside restriction
  • History of NG-tube or G-tube weaning
  • Growth concerns paired with strong food aversions, not just low intake
  • Formula or supplement dependence beyond the expected age

Do's & don'ts

Do

  • Loop in feeding therapy when education alone isn't moving intake
  • Coordinate on gut-brain factors — constipation and refusal are linked
  • Share labs and growth data with the feeding team (with consent)
  • Name the sensory/motor piece out loud to parents, not just the numbers

Don't

  • Push volume or calorie goals before sensory/motor barriers are addressed
  • Assume refusal is non-compliance
  • Recommend "one more bite" or finish-your-plate rules
Say this instead
"Your plan is solid — I think what's getting in the way is how his body is responding to the food itself. I want to bring in a feeding therapist to work on that piece alongside what we're doing."
03 · Counselors & Therapists

PFD can look exactly like ARFID or happen alongside ARFID— and you shouldn't have to tease them apart.

Pediatric Feeding Disorder often presents with the same anxiety, rigidity, and mealtime distress you'd expect from ARFID. But PFD has an oral-motor or sensory skill deficit underneath it — something that can only be accurately identified through oral-motor and sensory testing.

Red flags to screen for that might indicate this is not all psychological

  • Feeding anxiety has prgressed over years. There is usually a past history of feeding challenges early on since birth
  • Food avoidance is specific to textures or food groups. Look for patterns like avoiding harder to chew foods like meats and vegetables.
  • Child may have senosry sensitivites that extend beyond just food
  • There was not an identifiable traumatic event surrounding the food
  • Ask if the child has any of the following: extended chewing times, frequently spitting out food, chewing on one side of the mouth, or messy eating --these can be signs of oral motor or skill based defecits
  • Kids can go long periods of time without asking for food, rarely notice or complain of being hungry, or graze all day slowly.
  • Parents report bloating , excessive gassiness, distended belly, constipation, excessive vomiting, and frequent illness-- these can be signs the issue is more medically based.

Do's & don'ts

Do

  • Treat rigidity + food refusal as a reason to rule out a skill deficit, not just an anxiety diagnosis
  • Refer to a myofunctional therapist or an SLP with specific advanced oral-motor training who can accurately assess for a skill deficit
  • Coordinate co-treatment so exposure work and oral-motor work happen at the same time

Don't

  • Diagnose or rule out PFD yourself — it requires oral-motor, gut, and sensory testing
  • Refer to a generalized speech pathologist — you need someone with specific advanced oral-motor training, not general SLP scope
  • Treat food avoidance as purely behavioral or willpower-based
  • Assume that past feeding therapy has ruled out oral motor and gut issues. It is rare for parents to have received the full story and often have been dismissed by other professionals or have used a general therapist who wasn't trained to differntially diagnose these issue.
Say this instead
"This could be anxiety, or it could be that his mouth genuinely can't do what we're asking yet — and those need different specialists to tell apart. I want to get him in front of someone with advanced oral-motor training before we assume it's one or the other."
04 · OT / PT / Other SLPs

When a plateau in general therapy is actually a feeding-specific barrier.

Feeding draws on oral-motor, sensory, and postural systems all at once. If progress in general OT or PT isn't carrying over to the table, it's often worth a feeding-specific evaluation rather than more of the same intervention.

Red flags to watch for

  • History of tongue ties, open mouth breathing, snoring, and dental crowding
  • Sensory presentation extends beyond what a general sensory diet addresses
  • Gagging or choking at meals beyond what's typical for age
  • Articulation errors — especially R, L, or TH — that persist well beyond the typical developmental timeframe
  • Postural or positioning issues visibly affecting intake
  • Child has plateaued in general sensory/motor work with no change at the table
  • Suspected tongue tie or structural airway concern

Do's & don'ts

Do

  • Refer when progress plateaus specifically around eating, even if general therapy is going well
  • Refer persistent R/L/TH errors to someone with advanced oral-motor training and myofunctional therapy if general artic therapy isn't moving the needle
  • Collaborate on carryover between clinics — shared strategies stick better
  • Share the sensory profile and motor findings you already have

Don't

  • Treat articulation in isolation from the whole-body sensory/motor/feeding picture
  • Assume picky eating is outside your scope to flag, even if it's outside your scope to treat
Say this instead
"I see some red flags I think someone with more specilized training could be helpful with so we see greater success across the board."
05 · GI & Medical Specialists

Refer in parallel with the workup — not after everything's been ruled out.

Families often land in feeding therapy only after months of medical workups come back clear. Referring alongside the workup, rather than after it, gets families support faster and keeps behavioral patterns from setting in.

Red flags to watch for

  • Reflux or constipation workup is clear, but refusal persists
  • Post-tube-weaning transition needing feeding support
  • Parents report sensitivity to certain food despite allergist ruling out any food allergies
  • Growth faltering with no clear medical etiology
  • Child is eliminating a pattern of certain textures or food groups

Do's & don'ts

Do

  • Refer alongside the medical workup, not after it's "ruled everything out"
  • Refer to allergist to rule out black and white food allergies
  • Flag behavioral patterns early, before they become entrenched

Don't

  • Wait for a clean diagnosis before considering feeding therapy
  • Treat persistent refusal as purely a GI symptom once labs are normal
Say this instead
"Your labs look reassuring, and I still want to bring in a feeding therapist now — waiting doesn't usually make the mealtime piece easier to unwind."
06 · School & Daycare Staff

You often see the mealtime struggle before anyone else does.

What happens at the lunch table is some of the most useful information a family can get. You don't need to diagnose anything — just describe what you see and let the parent take it from there.

What to notice at mealtime

  • Child eats significantly less or differently at school than parents describe at home
  • Refuses to eat in front of peers, hides food, or shows distress at lunchtime
  • Rigid food rules — won't eat if foods touch, needs specific packaging or brands
  • Gags or vomits during meals in the classroom setting
  • Consistently sent home with an untouched lunch
  • Peers comment on or react to how the child eats

Do's & don'ts

Do

  • Share specific observations with parents — what, how much, how the child reacted
  • Let the child bring safe foods without comment or shame
  • Allow opportunities to practice exploring new foods when possible

Don't

  • Enforce a "no thank you bite" rule
  • Comment on how much a child ate in front of peers
  • Use dessert, stickers, or rewards tied to eating
Say this instead (to parents)
"I noticed [child] doesn't eat much at lunch and seems anxious around new foods — I wanted to flag it in case it's helpful."
07 · Dentists & Orthodontists

What you see in the mouth often is affecting speech or feeding.

Tongue thrust, narrow palates, and prolonged oral habits don't exist in isolation — they're frequently tied to the same oral-motor patterns driving a child's food refusal or speech impediment. You're often the first provider to spot the physical signs, well before a parent connects them to mealtime struggles.

Red flags to watch for

  • Tongue thrust or low resting tongue posture affecting bite development
  • High, narrow, or vaulted palate
  • Persistent mouth breathing or low tongue resting posture
  • Open bite, crossbite, or malocclusion
  • Strong gag reflex that interferes with exams
  • Prolonged pacifier, bottle, or thumb habit well past the expected age
  • Cavities concentrated in a child eating a very limited, carb-heavy, or highly processed diet
  • Child shows anxiety or resistance at the dentist that mirrors mealtime refusal patterns

Do's & don'ts

Do

  • Ask about feeding and speech history when you see tongue thrust, narrow palate, or persistent oral habits
  • Coordinate myofunctional therapy to work with any potential orthdontic work
  • Flag when limited diet — not just hygiene — looks like it's driving decay

Don't

  • Treat tongue thrust or open bite as purely mechanical/orthodontic without asking about feeding or speech
  • Recommend a tongue-tie release without coordinating myofunctional therapy before and after
  • Assume a parent's mention of picky eating is unrelated to what you're seeing in the exam
Say this instead
"I'm seeing some patterns here — tongue position, palate shape — that often go hand-in-hand with feeding and speech challenges. I want to bring in a feeding therapist or myofucntional speech pathologist to work on the oral-motor piece alongside what we're doing here."
What Happens After You Refer a Family

A structured pathway designed to uncover the root cause of feeding struggles.

One pathway, no matter who sends the family our way.

1

Comprehensive Evaluation

We evaluate oral-motor function, sensory processing, nutritional patterns, medical history, and mealtime dynamics — with food sensitivity and gut microbiome testing when clinically appropriate.

2

Targeted Implementation

Families move directly into 8 implementation sessions, turning findings into guided, practical progress through parent coaching and clear next steps.

3

Ongoing Support When Needed

For complex cases, twice-monthly support sessions continue — with the child included on calls when direct oral-motor work is needed.

Help Families Access Insurance Coverage

We provide physicians with a simple documentation template that can help support medical necessity when families pursue out-of-network reimbursement or a gap exception for feeding therapy.

Download Medical Necessity Template
  • ✔ Includes feeding disorder diagnosis codes
  • ✔ Includes gap exception request wording
  • ✔ Designed for pediatric feeding therapy referrals
Did You Know?
  • ⚠️ Picky eating affects up to 50% of children under 61
  • ⚠️ ARFID is estimated to impact 1–5% of children and teens — and often goes undiagnosed2
  • ⚠️ Pediatric Feeding Disorder affects more than 1 in 37 U.S. children under age 53
  • ⚠️ Feeding challenges often lead to nutritional deficiencies in iron, zinc, and key vitamins A, C, and B4,5,6
Without Extra Work

We make you the hero.

We're a specialized feeding therapy team that helps families get real answers and tangible progress — while making you look like the provider who connected the dots. When you refer to Foodology, here's what you can expect:

  • ✅ A thorough evaluation and action plan parents have been begging for
  • 🕒 Progress updates (with consent) — no extra admin for you
  • 💬 No pressure to "diagnose" outside your scope
  • 🙌 Confidence that tricky cases are being handled seriously and holistically

And the best part? You won't see that same family cycling through your office again and again with no plan.

Pediatrician examining a smiling young girl
Our Approach

The 4 Pillars of Feeding Success™

We don't just manage symptoms — we get to the root. Every evaluation and intervention runs through all four pillars.

Pillar 01

Oral-Motor Function

Chewing patterns, bolus formation, postural stability, and oral coordination — including structural issues like tongue tie that often go undetected.

Pillar 02

Sensory Processing

Over- and under-responsivity across the sensory systems that drive refusal, anxiety, or avoidance — matched to the child's regulation profile.

Pillar 03

Gut & Nutritional Health

Constipation, food intolerances, and nutrient gaps that affect appetite and regulation — addressed alongside functional providers.

Pillar 04

Feeding Mindset & Regulation

Co-regulation, play-based exposure, and nervous-system-informed strategies that rebuild safety, trust, and curiosity around food.

Feeding Disorders at a Glance

PFD, ARFID, or just picky?

Not all selective eating is the same — and not every child will grow out of it. These charts break down the key differences and what's typical at each infant feeding stage.

What Referring Providers Say

Trusted across specialties.

"This is exactly what I needed — clear, concise, and based on real feeding therapy experience. I keep it in my drawer for every 18-month and 2-year well check."

— Pediatrician, Long Island, NY

"I've referred multiple families to Foodology and every single one came back saying they finally felt heard. The reports are clear, actionable, and respectful of our role as providers."

— Pediatrician, Long Island, NY
Frequently Asked Questions

Questions from referring providers

Do I need to diagnose ARFID or PFD before referring?

Not at all. We handle the evaluation and differential process. Many children don't fit neatly into a diagnosis — that's where our whole-child approach shines. You simply refer based on concern.

Do you take insurance?

We're private-pay only, so we can provide the depth of evaluation and ongoing support complex cases need. We offer a downloadable Insurance Appeal Toolkit and customized superbills to help families pursue out-of-network reimbursement. Most services are also HSA/FSA eligible.

Can you work with families outside New York?

Absolutely. We provide virtual evaluations, coaching, and courses worldwide — feeding issues don't stop at state lines, and neither do we.

What happens after I refer a family?

We begin with a thorough intake, then guide the family to the next best step — a virtual or in-person evaluation, a detailed assessment across oral-motor, sensory, nutritional, and behavioral components, and a personalized plan of care. With parent consent, you'll receive a summary of findings and brief updates, without any extra paperwork on your end.

Questions About a Case?

Our clinical team is happy to help you decide if a referral makes sense.

Send parents directly to our Start Here page, or reach out to us to talk through a specific case.

Send Parents to the Start Here Page

Contact Us

📞 (516) 669-0434 📧 hello@foodologyfeeding.com 📍 2 Dubon Ct, Farmingdale, NY 11735
© 2026 Foodology Feeding Therapy. 2 Dubon Ct, Farmingdale, NY 11735 · (516) 669-0434

You’re doing everything you can. But you can’t do it all.

As a pediatrician, therapist, or school provider, you care deeply about your families — but feeding concerns? They’re messy, complex, and time-consuming.

You’ve probably been there:

  • A child eats five foods… but they’re still growing

  • A parent insists something is wrong… but you don’t see a clear medical diagnosis

  • You want to help… but you’re out of time, tools, or referrals

That’s where a trusted feeding therapy referral makes all the difference.

You want to support them. But you also don’t have 45 minutes to explain sensory feeding aversions, oral motor delays, or ARFID.

That’s where Foodology Feeding steps in.

What Happens After You Refer a Family

A structured pathway designed to uncover the root cause of feeding struggles and create meaningful progress for families.

1

Comprehensive Evaluation

We evaluate oral-motor function, sensory processing, nutritional patterns, medical history, and mealtime dynamics. When clinically appropriate, families also complete food sensitivity testing and a stool gut sample to assess microbiome health, permeability, and underlying contributors.

2

Targeted Implementation

Families move directly into an initial package that includes 8 implementation sessions, so they are never left trying to figure out what to do after the evaluation. This phase turns findings into guided, practical progress through parent coaching and clear next steps.

3

Ongoing Support When Needed

For more complex cases, families may continue with twice-monthly 45-minute support sessions. When direct oral-motor work with the child is needed, we include the child on calls as appropriate to support progress more directly.

Help Families Access Insurance Coverage

We provide physicians with a simple documentation template that can help support medical necessity when families pursue out-of-network reimbursement or a gap exception for feeding therapy.

Download Medical Necessity Template
✔ Includes feeding disorder diagnosis codes
✔ Includes gap exception request wording
✔ Designed for pediatric feeding therapy referrals

Providers may modify this template as needed based on clinical judgment and patient diagnosis.

For families you believe may benefit from a deeper feeding evaluation.

Questions About a Case?

Our clinical team is happy to help determine whether a feeding evaluation may be appropriate.

📞 +1 (516) 669-0434
📧 hello@foodologyfeeding.com

Did you know facts about feeding disorders in children

References for Feeding Statistics & Nutritional Impact

¹ Taylor, C. M., Wernimont, S. M., Northstone, K., & Emmett, P. M. (2015).
Picky/fussy eating in children: review of definitions, assessment, prevalence and dietary intakes. Appetite, 95, 349–359.
https://doi.org/10.1016/j.appet.2015.07.026

² Thomas, J. J., Lawson, E. A., Micali, N., Misra, M., Deckersbach, T., & Eddy, K. T. (2017).
Avoidant/restrictive food intake disorder: a three-dimensional model of neurobiology with implications for etiology and treatment. Current Psychiatry Reports, 19(8), 54.
https://doi.org/10.1007/s11920-017-0800-0

³ Goday, P. S., Huh, S. Y., Silverman, A., Lukens, C. T., Dodrill, P., Cohen, S. S., Delaney, A. L., Feuling, M. B., Noel, R. J., Gisel, E., Kenzer, A., & Browne, J. V. (2019).
Pediatric Feeding Disorder: Consensus Definition and Conceptual Framework. Journal of Pediatric Gastroenterology and Nutrition, 68(1), 124–129.
https://doi.org/10.1097/MPG.0000000000002188

⁴ Dovey, T. M., Staples, P. A., Gibson, E. L., & Halford, J. C. G. (2008).
Food neophobia and ‘picky/fussy’ eating in children: A review. Appetite, 50(2–3), 181–193.
https://doi.org/10.1016/j.appet.2007.09.009

⁵ Rucklidge, J. J., Johnstone, J., & Kaplan, B. J. (2014).
Nutrition and mental health: mainstreaming dietary treatment in clinical practice. The Lancet Psychiatry, 1(5), 400–402.
https://doi.org/10.1016/S2215-0366(14)70344-1

⁶ Kennedy, D. O. (2016).
B Vitamins and the Brain: Mechanisms, Dose and Efficacy—A Review. Nutrients, 8(2), 68.
https://doi.org/10.3390/nu8020068

We Make You the Hero

(Without Extra Work)

We’re a specialized feeding therapy team that helps families get real answers and tangible progress — while making you look like the provider who connected the dots.

When you refer to Foodology, here’s what you can expect:

A thorough evaluation and action plan parents have been begging for
🕒 Progress updates (with consent) — no extra admin for you
💬 No pressure to “diagnose” outside your scope
🙌 Confidence that tricky cases are being handled seriously and holistically

And the best part?
You won’t see that same family cycling through your office again and again with no plan.

You Get to Be the Provider Who Listened

The one who didn’t dismiss a parent’s gut feeling.
The one who offered real help.
The one who referred them to someone who could finally make a difference.

Let us take those “problem feeders” off your hands — and give you peace of mind that they’re getting the support they need.

Your Role Is Incredibly Valuable

Your referral might be the moment that changes everything.

We’ll handle the rest — thoroughly, respectfully, and with a holistic lens.
👇 Keep reading to see how we approach feeding — and when to refer.


Clinical Indicators for Feeding Therapy Referral

Children

If you’re unsure whether feeding therapy is warranted — these are the cases we specialize in.
Even when children are “growing fine,” the red flags below may indicate a deeper issue.

Refer if a child:

  • Eats fewer than 20 total foods

  • Eliminates entire food groups or textures

  • Refuses previously accepted foods (and doesn’t regain them)

  • Gags, vomits, or cries in response to food exposure

  • Insists foods be prepared exactly the same way

  • Shows extreme rigidity, anxiety, or panic at meals

  • Has ongoing constipation, reflux, or suspected food sensitivities

  • Is stuck at a feeding milestone (e.g., never progressed from purées)

  • Avoids eating in front of others or at school

  • Experiences distress when asked to try or even be near new foods

Infants

Feeding challenges start early — and they’re often missed or misdiagnosed.

We offer expert evaluations for infants with:

  • Difficulty latching or staying on the breast/bottle

  • Excessive spit-up, arching, or gas

  • Poor weight gain or feeding fatigue

  • Suspected tongue or lip ties

  • Transition issues to solids

We assess oral-motor function, guide families through feeding techniques, and provide referrals when bodywork is also needed.

Early feeding concerns don’t always go away on their own. A referral today can prevent bigger challenges later.

“Chart outlining which feeding concerns warrant a referral to Foodology. Includes columns for feeding issue types (e.g., limited variety, refusal, sensory aversions, oral-motor delays, gut symptoms), and matches them to appropriate provider referrals. Emphasizes that Foodology specializes in cases involving ARFID, PFD, sensory-based refusal, oral-motor challenges, and children who eat fewer than 20 foods.

Checklists and Tools for Pediatricians

ARFID/PFD

Spot the red flags. Know what’s normal. Refer with confidence.

Feeding issues are often dismissed or misclassified as “just picky eating.” But if left unaddressed, they can spiral into nutritional deficiencies, anxiety, ARFID, or Pediatric Feeding Disorder (PFD).

That’s why we created this simple, therapist-designed checklist — to help you:

✅ Identify when picky eating is no longer typical
✅ Understand which behaviors warrant referral
✅ Support parents without jumping to judgment or false reassurance
✅ Save time in appointments by having a clear decision-making tool

INFANTS

Catch feeding concerns before they spiral — even in babies.

Feeding difficulties can start long before solids — from latch issues to silent reflux to bottle refusal. And too often, infant struggles are dismissed as “normal” or blamed on parental anxiety.

Our Red Flags Brochure for Infants gives you a quick guide to:

✅ Recognize early signs of feeding dysfunction in babies
✅ Know when tongue tie, reflux, or bottle refusal may warrant referral
✅ Empower parents without adding pressure
✅ Avoid the “wait and see” trap that delays care

Designed to support faster decision-making at well visits — and help you refer with confidence, even in those tricky under-12-month cases.

Pediatrician Checklist (1)

📦 Want printed copies for your office? Just let us know — we’ll send them.

 “This is exactly what I needed — clear, concise, and based on real feeding therapy experience. I keep it in my drawer for every 18-month and 2-year well check.”
— Pediatrician in Long Island, NY

is your baby struggling with feeding brochure

Feeding Disorders at a Glance

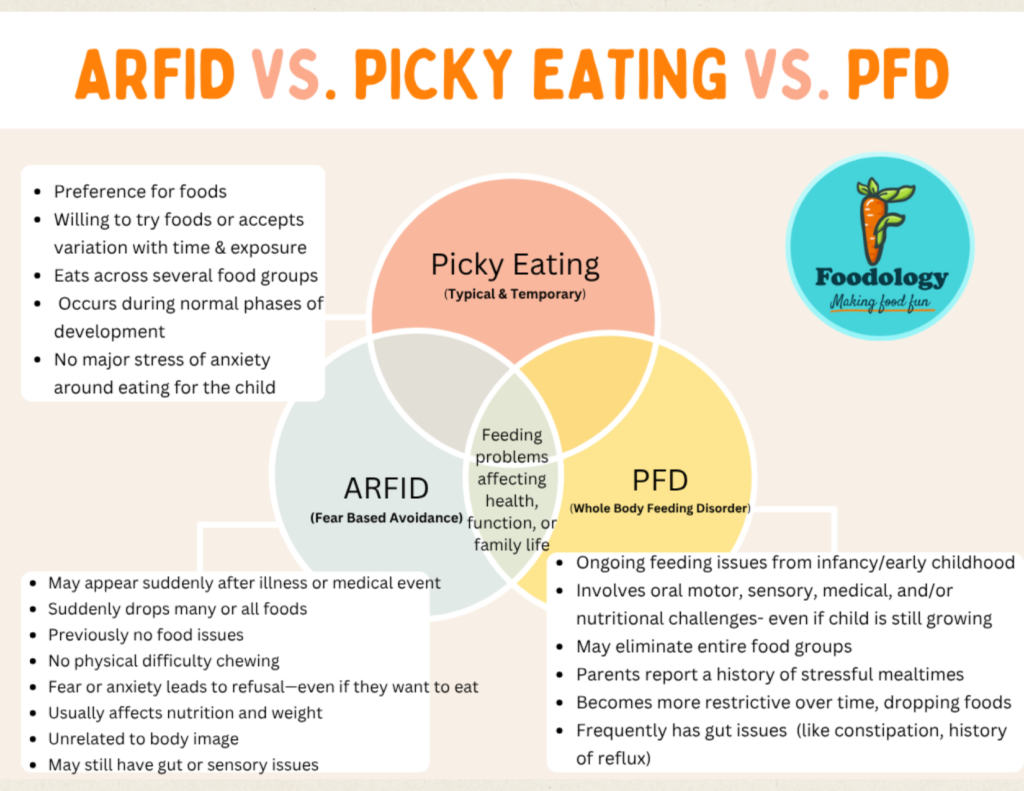
Venn diagram showing the differences and overlaps between picky eating, ARFID (Avoidant/Restrictive Food Intake Disorder), and Pediatric Feeding Disorder (PFD), highlighting behavioral, sensory, and medical feeding challenges in children

PFD, ARFID, or Just Picky?

Not all selective eating is the same — and not every child will grow out of it.

This diagram breaks down the key differences between developmental picky eating, ARFID, and Pediatric Feeding Disorder — so you can make informed referrals with confidence.

weight and picky eating

Infant Feeding: What’s Normal — and What’s Not?

Feeding challenges in infancy often go unrecognized — but early red flags can signal deeper issues.

This resource outlines the most common signs of infant feeding difficulty, including oral-motor concerns, reflux-like behavior, and delayed transitions to solids.

Know what’s typical… and when to refer.

Our Approach: The 4 Pillars of Feeding Success™

We don’t just manage symptoms. We get to the root.

At Foodology, we specialize in complex feeding cases by addressing the true source of mealtime struggles — not just the surface behaviors.
Our proprietary framework, The 4 Pillars of Feeding Success™, guides every evaluation and intervention.


 1. Oral-Motor Function

Subtle deficits can severely impact chewing, swallowing, or food variety — especially when structural issues (like tongue tie or jaw instability) go undetected.

➡️ We assess chewing patterns, bolus formation, postural stability, and oral coordination to uncover what others often miss.


2. Sensory Processing

Over- and under-responsivity across the 8 sensory systems — especially tactile, gustatory, and interoception — can drive refusal, anxiety, or avoidance.

➡️ We use sensory-informed strategies to match the child’s regulation profile and build food tolerance without pressure.


3. Gut & Nutritional Health

Constipation, food intolerances, histamine overload, and nutrient gaps all affect appetite, regulation, and mealtime success.

➡️ We collaborate with functional providers and use evidence-based strategies to support gut–brain balance and reduce internal distress.


4. Feeding Mindset & Nervous System Regulation

Feeding is relational. Trauma, anxiety, and nervous system dysregulation disrupt safety, trust, and curiosity around food.

➡️ We integrate co-regulation techniques, play-based exposure, and our signature subliminal audio tools to support rewiring at the subconscious level.


Together, these pillars allow us to differentiate between:

  • 🟡 Developmental picky eating

  • 🔴 ARFID (Avoidant/Restrictive Food Intake Disorder)

  • 🟣 Pediatric Feeding Disorder (PFD)

This whole-child lens is what sets us apart — and why we often see progress when traditional therapy has failed.

🌍 Available Worldwide
Whether you’re in New York or New Zealand, we offer virtual services for families across the globe — including evaluations, parent coaching, and online programs.

Testimonials

“We spent a year in feeding therapy with no results.”

“Nothing clicked until we worked with Christine. This program explained things no one ever had — and it actually worked. I wish we had started here first.”
Sarah, mom of a 5-year-old in the Fearful™ stage

“The only feeding referral I trust to get results.”

“I’ve referred multiple families to Foodology and every single one came back saying they finally felt heard. The reports are clear, actionable, and respectful of our role as providers.”
Pediatrician, Long Island, NY

Frequently Asked Questions

Do I need to diagnose ARFID or PFD before referring?

Not at all.
We handle the evaluation and differential process. Many children don’t fit neatly into a diagnosis — that’s where our whole-child approach shines. You simply refer based on concern.

We Fill the Gap That Insurance-Based Clinics Often Miss

Unlike most insurance-based therapy providers, we don’t just check a box or follow a 6-session template.
We specialize in complex, layered feeding cases — the ones that often get dismissed, delayed, or underserved in traditional systems.

That’s why we’re private-pay only — so we can provide the depth of evaluation, individualized planning, and ongoing support these families truly need.

But we also know cost matters.

We offer tools to help families access out-of-network reimbursement:

  • A downloadable Insurance Appeal Toolkit with ready-to-use templates and parent guides

  • Customized superbills that reflect medically necessary services and align with insurer language

Yes — most of our services are eligible for HSA/FSA payment. We also provide detailed receipts and documentation to support that process.

Absolutely.
We provide virtual evaluations, coaching, and courses worldwide — helping families across the U.S. and internationally. Feeding issues don’t stop at state lines, and neither do we.

Once the family contacts us, we begin with a thorough intake to understand the child’s feeding history, current challenges, and family goals.

We then guide them through the next best step — which may include:

  • A virtual or in-person evaluation based on location, severity, and support needs

  • A detailed assessment of oral-motor, sensory, nutritional, and behavioral components

  • A personalized Roadmap or plan of care that outlines how we will address root causes of feeding challenges

With parent consent, we’ll send you a summary of findings and next steps.
You’ll also receive brief, relevant updates — so you stay informed without additional paperwork or time taken from your day.

Our goal is to give your families the comprehensive support they need — and give you peace of mind that they’re in expert hands.

We specialize in:

  • Children who eat fewer than 20 foods

  • Infants with feeding difficulties (e.g., latch issues, poor transfer, oral motor concerns, poor weight gain, mom struggling to breasstfeed)
  • Kids with oral-motor delays, sensory sensitivities, or anxiety around eating

  • Families who’ve tried traditional therapy with little progress

  • Suspected ARFID or PFD

  • Parents who feel dismissed or desperate for answers

See other free resources

Refer parents to How to Un-Picky Your Picky Eater — a podcast hosted by Christine Miroddi Yoder, pediatric feeding expert and founder of Foodology. Each episode offers practical, holistic tips to help parents reduce mealtime stress and support their child’s relationship with food.

LISTEN TO PODCASTS

Our blog covers evidence-informed insights into Pediatric Feeding Disorder, ARFID, and picky eating.

Explore practical articles you can share with parents or use to guide conversations during well visits and therapy sessions.

EXPLORE ARTICLES

Food Introduction Protocol

Help your child explore one new food in just five days—without pressure, bribing, or mealtime battles. Get the free step-by-step Food Introduction Protocol™.


Food INtroduction Protocol

This will close in 20 seconds